


Alcohol and Nerve Regeneration: Why Your Evening Drink is Harming Your Extremities
Discover how alcohol and nerve regeneration are blocked by evening drinks. Learn how ethanol depletes B-vitamins and harms your extremities.
Understanding diabetes mellitus pathophysiology requires a comprehensive look at cellular receptor mechanics, pancreatic beta-cell kinetics, hepatic gluconeogenesis, and peripheral tissue starvation. The complex diabetes mellitus mechanism begins when target cells fail to clear glucose efficiently from systemic circulation, triggering a cascade of progressive metabolic malfunctions. By analyzing insulin resistance pathophysiology alongside hormonal drivers, clinicians can intercept microvascular complications before irreversible organ tissue damage occurs.
Examining the pathology of diabetes reveals how persistent hyperglycemia damages vascular endothelial cells through oxidative stress and advanced glycation end-products (AGEs). The fundamental pathophysiology of dm involves both absolute insulin deficiency and peripheral tissue unresponsiveness. To build a solid clinical foundation, review our primary hub, the Diabetes Management Guide, along with The Ultimate Diabetes Guide 2026.
During diagnostic screening, patients frequently ask: is fasting insulin the same as A1C? While A1C reflects a 90-day average percentage of glycated hemoglobin, fasting insulin measures immediate endocrine secretory effort. Evaluating these markers alongside early warning signs of diabetes gives a clear, objective picture of a patient's metabolic trajectory over time.
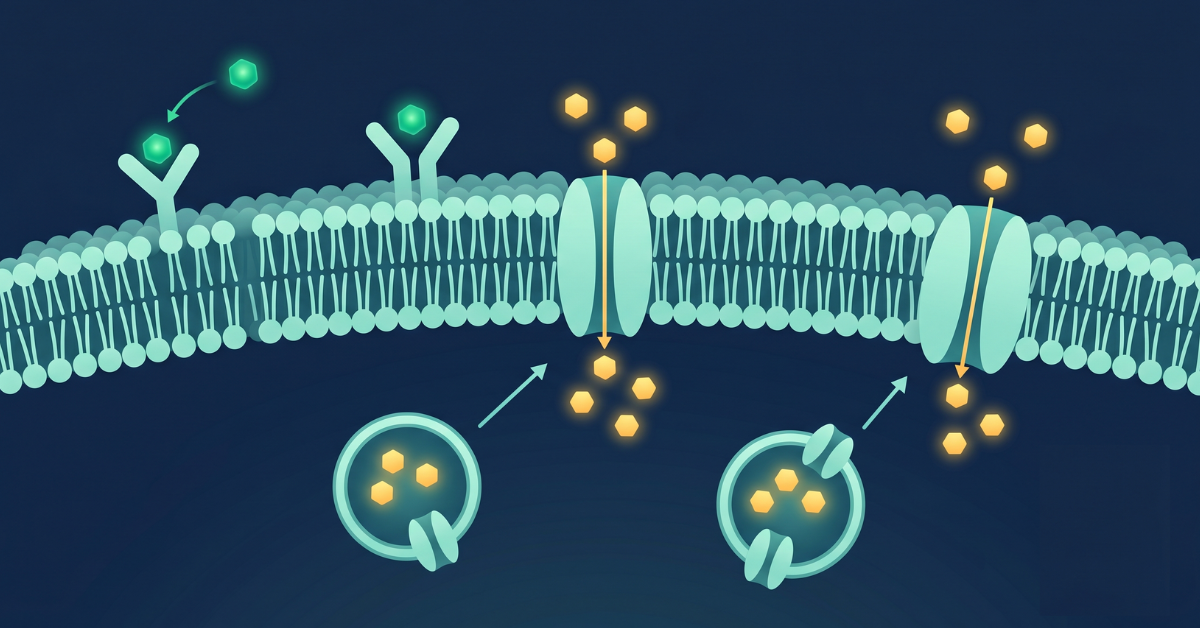
At the microscopic level, diabetes mellitus pathophysiology is defined by a severe breakdown in transmembrane signaling protocols. In a healthy human homeostatic environment, pancreatic beta cells continuously monitor circulating blood glucose concentrations. When glucose rises following meal digestion, beta cells release insulin into the bloodstream. Insulin then binds to the alpha-subunits of insulin receptors on target muscle, fat, and liver tissue cells, activating intracellular tyrosine kinase activity.
However, when studying insulin resistance pathophysiology, this intracellular cascade becomes severely blunted. Free fatty acid accumulation, pro-inflammatory cytokines (such as TNF-alpha and IL-6), and chronic hyperinsulinemia cause serine phosphorylation of insulin receptor substrate-1 (IRS-1). Consequently, glucose transporter-4 (GLUT4) vesicles remain trapped inside the cytoplasm instead of translocating to the cell membrane.
Without active GLUT4 transporters on the cellular surface, circulating glucose cannot enter skeletal muscle and adipose tissues. This core diabetes mellitus mechanism creates a dangerous paradox: while blood plasma is saturated with glucose, intracellular compartment starvation triggers systemic distress signals.
Understanding these underlying shifts in diabetes physiology allows clinicians to design targeted protocols that restore receptor sensitivity. When glucose clearance drops sharply, patients experience acute metabolic instability. To review acute management protocols, read our emergency guide on how to lower sudden high blood sugar quickly.
The global clinical pathology of diabetes is categorized by major international medical bodies, including the American Diabetes Association (ADA) and the World Health Organization (WHO), into distinct physiological categories based on underlying etiology:
In Type 1 diabetes, the primary pathophysiology of dm stems from an autoimmune destruction of pancreatic islet beta cells. Autoantibodies targeting glutamic acid decarboxylase (GAD65), islet antigen-2 (IA-2), and insulin result in complete endogenous insulin deficiency. Patients require lifelong exogenous insulin replacement to sustain basic metabolic processes and prevent diabetic ketoacidosis (DKA).
Accounting for over 90% of global cases, Type 2 diabetes mellitus pathophysiology involves a dual-defect mechanism: severe peripheral insulin resistance combined with progressive beta-cell secretory exhaustion. Visceral adiposity releases toxic lipid metabolites that impair receptor sensitivity. Exploring evidence-based clinical protocols on how to reverse type 2 diabetes reveals that substantial weight loss and caloric restriction can reduce ectopic liver/pancreatic fat, helping restore beta-cell function.
Developing during the second or third trimester of pregnancy, GDM occurs when placental hormones (human placental lactogen, progesterone, cortisol) induce marked peripheral insulin resistance in the mother. If pancreatic secretory compensation falls short, maternal hyperglycemia develops. Adopting a structured gestational diabetes diet plan is essential to control postprandial glucose surges and protect fetal growth.
Regardless of the specific etiology, unmanaged diabetes mellitus pathophysiology leads to systemic microvascular damage (retinopathy, nephropathy, neuropathy) and macrovascular complications (atherosclerosis, myocardial infarction, stroke).
A critical milestone in the progression of diabetes mellitus pathophysiology is the transition from initial hyperinsulinemic compensation to beta-cell failure. In the early stages of insulin resistance, pancreatic beta cells hyper-secrete insulin to overcome peripheral receptor resistance and maintain normal blood glucose levels.
However, over time, sustained metabolic overload induces severe endoplasmic reticulum (ER) stress and mitochondrial dysfunction within islet cells. This secondary phase of diabetes mellitus pathophysiology is accelerated by two distinct pathological processes:
Together, glucolipotoxicity leads to a progressive decline in functional beta-cell mass. As beta-cell capacity drops, endogenous insulin secretion can no longer offset peripheral resistance, turning subclinical prediabetes into overt Type 2 diabetes.
The liver plays a central role in maintaining systemic glycemic homeostasis. In a healthy fasting state, the liver breaks down stored glycogen (glycogenolysis) and synthesizes new glucose from amino acids and glycerol (gluconeogenesis) to supply glucose to the brain and red blood cells. When food is ingested, rising insulin levels signal the liver to stop glucose production and store surplus energy as glycogen.
In severe diabetes mellitus pathophysiology, hepatic insulin resistance disrupts this regulatory feedback loop. Even when circulating blood glucose and insulin concentrations are high, the liver misinterprets cellular starvation signals and continues uninhibited gluconeogenesis.
This uninhibited hepatic glucose output drives up fasting blood sugar levels, worsening morning hyperglycemia. Managing hepatic fat accumulation and supporting liver insulin sensitivity are essential steps in stabilizing daily glycemic baselines.
Endocrine hormones heavily influence daily glycemic fluctuations. A major factor driving early morning blood sugar spikes is the relationship between morning cortisol and blood sugar dynamics. As part of natural circadian rhythms, the hypothalamic-pituitary-adrenal (HPA) axis releases cortisol between 4:00 AM and 8:00 AM to prepare the body for waking.
Cortisol acts as a counter-regulatory hormone that stimulates hepatic gluconeogenesis and induces temporary peripheral insulin resistance. In healthy individuals, the pancreas secretes additional insulin to offset this cortisol surge, keeping waking glucose stable.
However, in diabetes mellitus pathophysiology, pancreatic secretory failure prevents this compensatory response. Consequently, cortisol drives fasting glucose levels upward before breakfast—a clinical pattern known as the Dawn Phenomenon.
To better understand these waking glucose spikes, read our comprehensive guide on why fasting blood sugar is high in the morning. Chronic psychological and physiological stress amplifies this response; learn how to offset stress-induced spikes in our detailed analysis of stress and blood sugar levels.
Sleep deprivation also aggravates HPA-axis dysfunction and impairs glucose tolerance. For a deep dive into sleep-related metabolic disruptions, explore our guide on how sleep deprivation affects fasting blood sugar.
Lifestyle factors can significantly worsen underlying diabetes mellitus pathophysiology. A common question patients ask clinicians is: does smoking increase blood glucose levels? Clinical studies consistently show that cigarette smoking directly worsens systemic insulin resistance and impairs glucose clearance.
Nicotine stimulates the sympathetic nervous system, triggering the release of catecholamines (epinephrine and norepinephrine) and cortisol. These hormones block insulin action in skeletal muscle and stimulate hepatic glycogen breakdown. Additionally, toxic compounds in tobacco smoke generate systemic oxidative stress and endothelial inflammation, aggravating microvascular complications.
Read our full clinical breakdown in how smoking affects blood sugar levels in diabetics. Other lifestyle choices also alter glycemic control; for example, explore how alcohol affects blood sugar levels in diabetics or learn why blood sugar spikes after exercise in diabetics.
Accurate diagnostic evaluation is essential for tracking diabetes mellitus pathophysiology and assessing therapeutic progress. A frequent point of confusion during laboratory screening is the difference between fasting plasma glucose vs fasting blood glucose.
Fasting plasma glucose (FPG) is measured in venous blood plasma drawn in a clinical laboratory setting after an 8- to 12-hour fast. In contrast, capillary fasting blood glucose is measured using whole blood drawn via a fingerstick on a handheld point-of-care glucometer. Because red blood cells extract glucose from whole blood, laboratory plasma glucose readings run roughly 10% to 12% higher than fingerstick glucometer values.
Another crucial diagnostic question is: is fasting insulin the same as A1C? These tests assess completely different aspects of metabolic health:
| Diagnostic Marker | Physiological Target | Clinical Insight |
|---|---|---|
| Fasting Insulin | Circulating hormone levels | Detects pancreatic hyper-secretion and insulin resistance years before blood sugar rises. |
| HbA1c Test | Glycated hemoglobin % | Provides a 90-day average of overall blood glucose control. |
| Fasting Plasma Glucose (FPG) | Venous plasma glucose | Standard lab diagnostic metric; values >=126 mg/dL indicate diabetes. |
Evaluating these markers together helps clinicians catch early metabolic shifts, assess beta-cell reserve, and tailor dietary and medical strategies to slow or reverse disease progression.
Alongside evidence-based dietary modifications, targeted botanical supplements can support insulin receptor sensitivity and help manage diabetes mellitus pathophysiology.
Support your diabetes mellitus pathophysiology management with 8 liquid adaptogens formulated to target cellular insulin resistance and support energy levels. Includes clinical botanicals like Eleuthero for Diabetes Fatigue, Coleus Forskohlii Blood Sugar, and Maca Root Energy Blood Sugar balance. Evaluated as our top best supplement for blood sugar support, or explore our review on the best blood sugar support supplement options.
Explore our full collection of clinical guides on diabetes physiology, hormonal mechanisms, and lifestyle management:
Managing diabetes mellitus pathophysiology effectively requires a coordinated, multi-target strategy that combines cellular insights, diagnostic monitoring, and targeted lifestyle modifications. Understanding the diabetes mellitus mechanism empowers patients and clinicians to make informed decisions that prevent long-term microvascular complications.
To continue exploring clinical guides, visit our central Diabetes Management Guide hub or review The Ultimate Diabetes Guide 2026 to support your long-term health journey.
Get instant access to your printable meal plan designed to balance carbohydrate intake and support daily glycemic stability.
Discover how alcohol and nerve regeneration are blocked by evening drinks. Learn how ethanol depletes B-vitamins and harms your extremities.

Explore how excessive dietary sodium and processed foods impair vascular microcirculation, increasing nerve pain and extremity numbness.

Discover how artificial sweeteners worsen neuropathy and why energy drinks disrupt nerve signal transmission. Protect your extremity health today.

Explore how artificial trans fats and hydrogenated processed oils degrade structural myelin membranes, starving nerve cells of proper electrical insulation.

Discover how smoking and nicotine constrict nerve blood supply through microvascular damage. Learn how tobacco worsens neuropathy symptoms.

Uncover the common daily foods that silently damage your nervous system, trigger blood sugar spikes, and worsen neuropathy symptoms.